


Who Was India's Healthcare Built For?
India has spent eight decades bringing healthcare within reach. But roads, trust, gender and the freedom to be sick still determine who can actually use it.
18 September 2026· 5 min read
TL;DR
India's healthcare system, built over eight decades, faces a critical inquiry: "Who was it truly designed to serve?" Despite remarkable gains in life expectancy, equitable access remains a profound challenge. The article highlights how socio-economic realities, particularly gender and the undervaluing of women's labour, dictate healthcare-seeking behaviours, often compelling delayed care. While the ambitious 1946 Bhore Committee laid a blueprint for primary health centres, implementation consistently faltered, leading to understaffing and reliance on informal practitioners. This persistent gap, despite initiatives like ASHA workers, reveals a system grappling with inherent design flaws and societal barriers that leave many unprioritised.
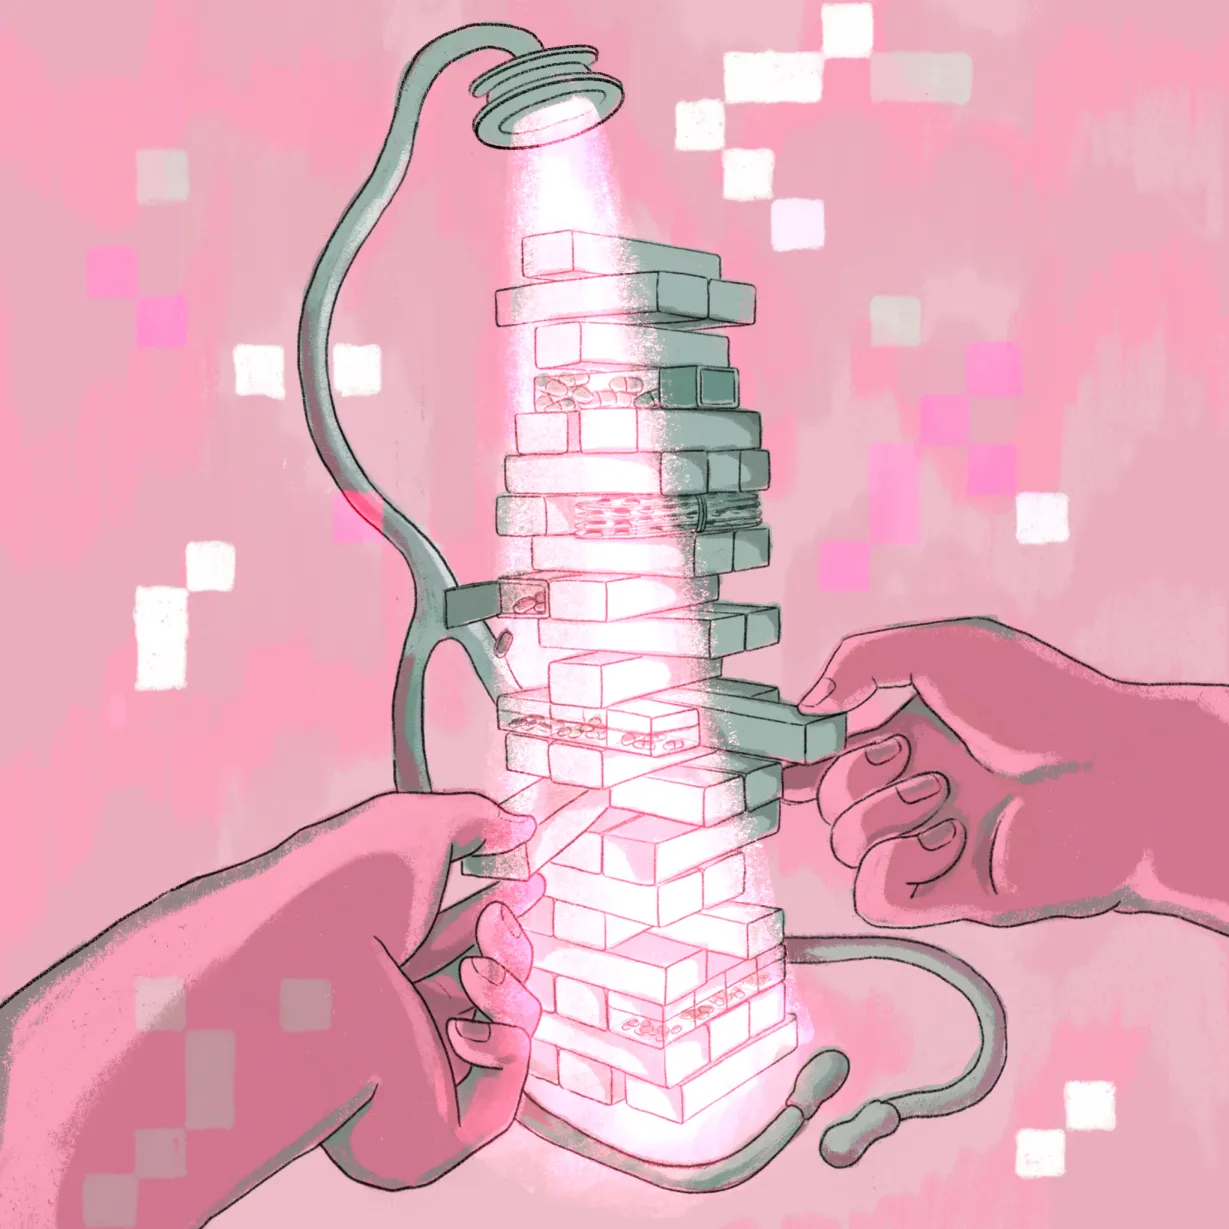
An ASHA worker in a village called Ira, in Karnataka’s Dakshina Kannada district, told a researcher that women in her village wait when they feel unwell. They wait until the illness gets worse before they see anyone.
Men don't wait. They take a pill from the local shop and move on.
Neither choice is a good one. But both are shaped by the same constraint. In a single-income household, a sick man means a lost wage. A woman's work is different. Housework has never been counted as work at all. So she keeps going, sick or not. She is expected to push through.
And no matter how good the hospital is, or how close the health centre is, none of it matters if the patient never chooses to walk in.
How do you solve a health problem the patient isn't allowed to prioritise?
That single observation is really a story about design. Someone always decides who a health system is built around. Who to encourage to come in and who is left to wait.
Trace India’s healthcare choices from 1946 to today, and that is what you find: one long, unfinished argument over who the system is really built for.
The blueprint
In 1946, a committee led by Sir Joseph Bhore surveyed a country where average life expectancy was just 27 years.
By independence, it had risen to 32. Most Indians alive in 1947 could expect to be dead before they turned 33. The committee's answer was ambitious. It proposed one primary health centre for every 40,000 people. Each would be staffed by a new kind of generalist, a “social physician,” trained in prevention as much as cure.
It was a design philosophy. The first health centre under the plan opened only in 1952. It was the first of many gaps between blueprint and brick that would recur through this story.
What did close, closed dramatically. Life expectancy today stands at 72 years.
Who the blueprint missed
A norm of one centre for every 40,000 people assumes those 40,000 people can actually reach it, and that the centre has enough people inside it to see them.
Bhore’s short-term plan, the one that actually got built, called for one health centre per 40,000 people, staffed by two doctors, a nurse, and a dozen other health workers, midwives, sanitary inspectors, dais. That was already the modest option. The committee’s real ambition, a 75-bed primary health unit for every 10,000 to 20,000 people, stayed in the report. Even the modest version has struggled to survive: many of today’s primary health centres run with a single doctor, sometimes none.
This gap was filled in different ways and in different spaces.
Informally, first, and not always for lack of a doctor. The jhola chap, the unqualified “bag-carrying” doctor, fills the space left by absence, and sometimes just by distrust. Doctor density in urban India is still roughly four times that of rural India, but even where a real doctor does show up, arriving doesn't mean arriving with anyone’s confidence. It’s the same tension Amazon Prime’s Gram Chikitsalay dramatizes—city doctor competing with the local quack everyone already knows.
Formally, elsewhere, China tried closing a similar gap by making the workaround official instead of leaving it informal. Starting in 1968, Mao’s government trained roughly a million “barefoot doctors”, farmers given basic medical instruction and sent back to treat their own neighbours between shifts in the fields. It wasn't real medicine, but it was resourced, trained, and counted as part of the system—unlike India’s jhola chaps, who fill the same gap with none of the three. Infectious disease deaths in rural China fell sharply through the 1970s. India built its own formal version much later, the ASHA worker—an Accredited Social Health Activist. But it never fully closed the older, informal gap the jhola chap still occupies.
The gap is also filled by individuals, when nobody official showed up at all.
In 1959, Dashrath Manjhi, a labourer in Bihar, lost his wife after she fell on the path over the Gehlour ridge separating their village from the nearest hospital, a journey of roughly 55 km around the hill. He spent the next 22 years carving a road straight through the rock. Alone. With a hammer and chisel. When he finished, the same journey was 15 km.
Nearly 70 years later, in June 2026, Sangeeta Gedam died after childbirth complications in a hamlet on the Maharashtra-Telangana border, because the ambulance sent for her couldn’t reach a village with no proper road. Her husband, Tulsiram Gedam, organised the village to build one themselves—1.5 km, by hand—rather than wait any longer for the state to do it. Different villages, different decades, a different kind of death. The same design gap still open in places.
Designing from the ground up
A scheme can fail the moment it forgets how people actually decide to trust it.
Take the fight against polio. By the early 1990s, the vaccine itself was the easy part. Getting people to trust it was the real fight.
In parts of Uttar Pradesh and Bihar, rumours travelled faster than any vaccinator. That the drops caused infertility. In the worst-affected pockets of Uttar Pradesh, close to one in ten households skipped the vaccine outright, and the disease clustered exactly where the fear did. So the programme had to design around distrust itself.
Vaccinators were drawn from the communities they served. Many were women who could sit inside another woman's home in a way a stranger from the block office never could.
Where clerics had once preached against the drops, workers kept showing up and talking. Over time, many of those same communities began announcing the next vaccination round over loudspeakers.
On television, Amitabh Bachchan held up two fingers.
“Do boond zindagi ke.”
Two drops of life.
With that, a health instruction became a shared ritual. Every vaccinated child left with a small black mark on a fingernail. Quiet proof for the next volunteer walking the same lane. It took two decades of this door-to-door persuasion before India, a country that once accounted for 60% of the world's polio cases, was declared polio-free in 2014.
The same instinct shaped two quieter revolutions.
Design for the person in front of you, not the population average.
In 1976, ophthalmologist Dr Govindappa Venkataswamy opened Aravind Eye Hospital, an 11-bed clinic in Madurai, Tamil Nadu. His inspiration was an unlikely one. He had studied Ray Kroc’s McDonald’s, even visiting the company’s Hamburger University in Chicago, to see how it delivered the same product, at the same standard, everywhere, at enormous scale. Could cataract surgery work the same way?
It did. What started as one rented house is now a network of a dozen hospitals in Tamil Nadu, together responsible for millions of surgeries since. Aravind’s surgeons average 2,000 operations a year each, against a national average of 400. Around 60% of its services are provided free, cross-subsidised by the patients who pay.
Around the same time in Jaipur, a craftsman and an orthopaedic surgeon built the Jaipur Foot. A $40 prosthetic designed for barefoot, squatting, muddy-field Indian life. It is now fitted across a dozen countries.
The success of both came from the same idea. They were designed for the body in front of them.
The rest of the story
By the ministry's own measures, healthcare design keeps improving.
Maternal mortality is down more than 80% since 1990. According to the National Health Accounts estimates, out-of-pocket health spending has fallen from 64% in 2013-14 to 39% of total health expenditure in 2021-22, though it has crept back up since.
Who is allowed to use it has changed much more slowly.
The Ayushman Bharat scheme now covers 12 crore of India’s poorest families through insurance, alongside a separate network of primary care centres, the Ayushman Arogya Mandirs. It’s real progress and by design, coverage for the poorest. The gap between what was proposed in 1946 and what exists now is eighty years of separate decisions.
Every layer of this story was a decision about who counted as the patient in front of someone. The 40,000-person norm, the ASHA worker on her cycle, Dr Venkataswamy’s assembly line and Ayushman Bharat's insurance card. Each one solved something real.
The number worth remembering isn’t 32 or 72. It’s the gap between them, and how much of it closed because someone refused to leave it standing—a labourer with a hammer, a vaccinator working door to door for two decades, a doctor who thought a burger chain had something to teach a hospital. What a system set out to solve, whom it actually serves, who still gets left out and whether the original answer still holds. Eighty years in, we ask all four questions at once.
The gap has never closed evenly and it has never stopped closing, either.
This is the second piece in the By Design series, which looks at the everyday systems around us, asking who built them, for whom, and who got left out.
About the illustrator
Purvi Ramtilak is a design student at BITS Design School, Mumbai, with an interest in telling stories through visual media. She is drawn to the way images can bring people together and make complex ideas feel more immediate.
Join the conversation
Nandita Abraham
Founding Dean | BITS Design School, Mumbai
Nandita Abraham is the Founding Dean of BITS Design School, Mumbai, under the aegis of BITS Pilani, an “Institution of Eminence”, where she leads efforts to revolutionise design education through collaboration, sustainability, and transdisciplinary learning.
With three decades in design education and institutional leadership, and global exposure spanning the US, Hong Kong, and India, she brings together expertise from the creative industries and academia. Her writing extends the same lens to systems beyond the classroom and leadership in higher education.
She has led the Tihar Jail Fashion Project, training over 300 inmates towards sustainable livelihoods, the Dastkar Ranthambore project, which rehabilitated people from three displaced villages, and Sewa Learning Centres, among other initiatives. The same instinct now shapes how she builds curriculum and leads institutions at BITS Design School: design judged by who it reaches, not by what it intended.
She serves on the FICCI National Higher Education Committee, holds Independent Director positions on corporate boards, and has held leadership roles at IFFTI and the CII National Design Committee. She has lectured at Northumbria University, the University of Delaware, and London College of Fashion, and presented at institutions and conferences across the US, the UK, Europe, Asia, and Australia.
Beyond the noise is the signal.
FF Insights: Sharpen your edge, Monday–Friday.
FF Life: Culture, ideas and perspectives you won't find elsewhere — Saturday.

Founding Fuel is sustained by readers who value depth, context, and independent thinking.
If this essay helped you think more clearly, you may choose to support our work.

Founding Fuel is sustained by readers who value depth, context, and independent thinking.
If this essay helped you think more clearly, you may choose to support our work.
Loading comments...
More by Nandita Abraham
Readers also liked

·Technology & the Future
Who Builds the Next Bhabha Movement?
Can India build a new compact between the state, science, industry and entrepreneurs?
SR

S. Raghotham
Journalist and strategic analyst
Who Builds the Next Bhabha Movement?
Can India build a new compact between the state, science, industry and entrepreneurs?
Journalist and strategic analyst

·FF Life
Oscar Predictions 2026: Who Will Win—and Why
My annual curtain-raiser: the likely winners, the dark horses, and the one film you should actually watch.
RR

Ronaan Roy
Former Deputy General Manager | Mahindra
Oscar Predictions 2026: Who Will Win—and Why
My annual curtain-raiser: the likely winners, the dark horses, and the one film you should actually watch.
Former Deputy General Manager | Mahindra

·FF Life
Who Gets to Decide What Happens at the End of Your Life?
Living wills remain on the fringes, but they are forcing India to confront family power, cultural taboo, and the realities of end-of-life care—signalling a profound shift in how the country thinks about dignity and medical decision-making
SB

Sveta Basraon
Editor and Head of Operations | Founding Fuel
Who Gets to Decide What Happens at the End of Your Life?
Living wills remain on the fringes, but they are forcing India to confront family power, cultural taboo, and the realities of end-of-life care—signalling a profound shift in how the country thinks about dignity and medical decision-making
Editor and Head of Operations | Founding Fuel
Explore more
Dive into other themes from our network.







